
How we make money: Some links on this page are affiliate links, marked “Sponsored.” If you buy through one, we may earn a commission. It doesn’t change what we write. This article is general information, not medical advice.
SI joint fusion is surgery that permanently joins the bones at one of your sacroiliac (SI) joints, where the base of your spine meets your pelvis.[1] It’s rarely needed for sacroiliitis, an inflamed SI joint. Doctors consider it for long-lasting SI joint pain that hasn’t improved with physical therapy and other nonsurgical treatment.[1][2] This guide explains how the operation is done, who it’s for, the risks, what recovery involves and what the research shows, including a trial that compared fusion with sham surgery.
In brief
- SI joint fusion is kept for severe, persistent SI joint pain that hasn’t responded to less invasive care, in people whose SI joint problem has been confirmed.[3][4]
- Most fusions are now minimally invasive, with metal implants placed through small cuts. Risks include infection, implant problems and pain that doesn’t go away.[1][3][5]
- Trials against nonsurgical care favored fusion, but the largest was sponsored by the implant maker, and a double-blind trial against sham surgery found no clear difference at 6 months.[6][7]
What is SI joint fusion?
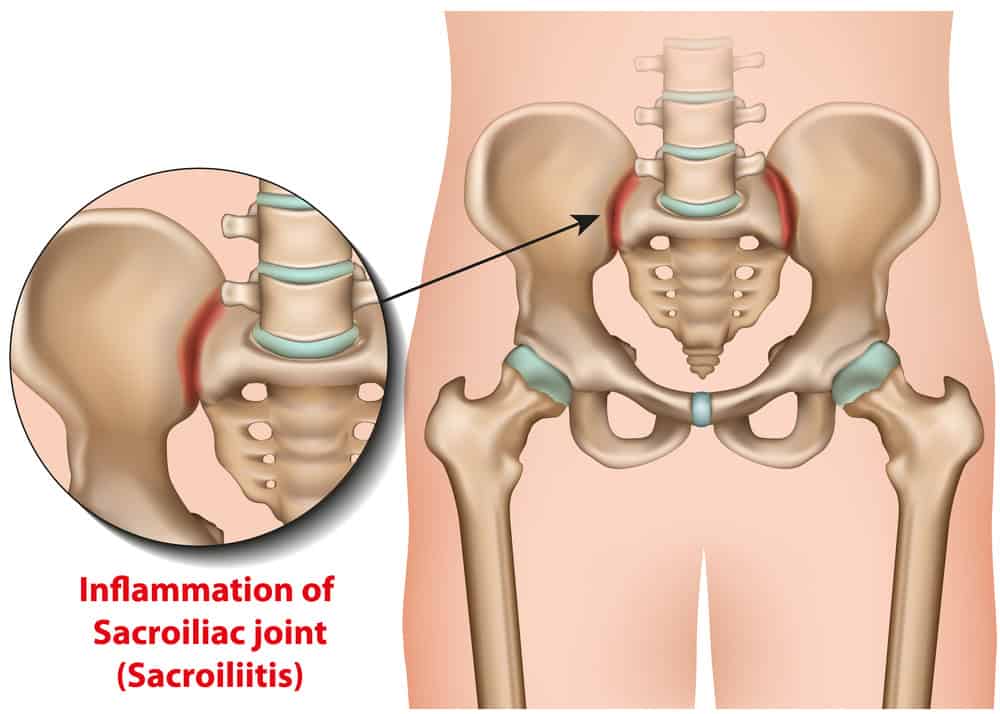
You have two SI joints, one on each side of the base of your spine. Each joins the sacrum, the triangle-shaped bone at the bottom of your spine, to the ilium, the upper part of your pelvis.[1] Fusion surgery, also called arthrodesis, fixes the bones of one joint together. As you heal, the bones are meant to grow together and become one, which makes the joint more stable.[1] In practice the bone doesn’t always grow across the joint, as the risks section below explains.[3] You may also see the operation called sacroiliac fusion or SI fusion.[1]
For how the joint works and what causes SI joint pain in the first place, see our guide to SI joint pain.
Minimally invasive and open fusion
There are two main forms. Minimally invasive fusion uses smaller cuts and usually means a quicker recovery. Open surgery uses larger cuts and is often kept for more complex cases.[1] Open fusion has been linked with long hospital stays, substantial blood loss and a high complication rate, and minimally invasive fusion now accounts for more than 90% of fusions for long-term SI joint pain.[5]
In minimally invasive fusion, surgeons can reach the joint from the side (a lateral approach), from behind (posterior) or at an angle between the two (posterolateral). A 2025 review found that pain relief and fusion rates looked similar across the three. The approaches hadn’t been compared head to head, though, the review rated the quality of its pooled evidence as very low, and all three randomized trials it found used the side approach. It also found the side approach might carry a higher risk of complications and revision surgery, again on very low-quality evidence.[8] NICE, the UK’s National Institute for Health and Care Excellence, notes that more than one device and approach is in use, but most of the evidence it reviewed came from one device placed from the side.[3]
What usually comes before surgery
Nonsurgical care comes first. Physical therapy is the most common treatment for sacroiliitis. Doctors also use anti-inflammatory painkillers (NSAIDs), muscle relaxers and steroid injections into the joint, and less often radiofrequency ablation, which stops nerves in the joint sending pain signals.[2] A 2025 review describes care as moving from physical therapy, lifestyle changes and NSAIDs to injections and radiofrequency treatment, with fusion kept for severe pain that hasn’t eased with less invasive options.[4] Our guide to SI joint injections covers that step in more detail.
Day-to-day steps for SI joint pain
The NHS’s general advice for back pain includes staying active and keeping up your daily activities, using an ice pack or a heat pack wrapped in a towel, and not staying in bed for long periods. If you try exercises and stretches for back pain, stop if your pain gets worse and get advice from a doctor.[9] A review of SI joint care adds avoiding activities that aggravate the pain and keeping your body weight down, and says an SI belt or brace might reduce stress on the joint and pain.[4] For movement, see SI joint pain exercises and the exercises to avoid. For nights, see how to sleep with SI joint pain.
Who is SI joint fusion for?
NICE says people having minimally invasive SI joint fusion should have a confirmed diagnosis of SI joint dysfunction, on one or both sides, caused by degenerative sacroiliitis or SI joint disruption. Surgery is considered for persistent symptoms that haven’t responded to nonsurgical treatment.[3] Cleveland Clinic describes the typical candidate as someone with ongoing lower back pain or sacroiliitis that hasn’t improved with nonsurgical treatments.[1]
Confirming the diagnosis matters. SI joint pain shows up in varied and unclear ways, so it’s hard to diagnose. Doctors use physical tests that press on or stress the joint, and an image-guided injection of local anesthetic into the joint has long been treated as the gold standard.[4] The sham-controlled trial described below only included people whose diagnosis had been confirmed with an SI joint injection.[7]
Before surgery, your provider and surgeon will ask how much your symptoms affect your daily life, which nonsurgical treatments you’ve tried and how well they worked.[1] NICE calls the procedure technically challenging and says it should only be done by surgeons who regularly use image-guided surgery to place implants and who have specific training in this operation.[3]
What happens during the surgery
Cleveland Clinic describes the operation in these steps:[1]
- You’re given general anesthesia, so you’re asleep and won’t feel pain. NICE notes that spinal anesthesia is sometimes used instead.[1][3]
- You lie face down on your stomach.[1]
- The surgeon makes cuts in the skin around the joint, usually only a few inches long.[1]
- Damaged cartilage and bone are removed.[1]
- Titanium implants are passed through the ilium into the sacrum, across the joint, and secured in place.[1]
- The cuts are closed.[1]
In the side approach that NICE describes, the surgeon works through a small cut in the buttock, guided by live X-ray images, and uses 2 or 3 metal implants, most often 3.[3] The operation usually takes around an hour. It’s usually an outpatient procedure, which means you go home the same day.[1]
SI joint fusion risks and complications
Cleveland Clinic lists infection, bleeding, pain and reactions to anesthesia as possible problems soon after surgery, and says they’re rare.[1] Other possible problems include:
- A failed fusion. Pain that doesn’t get better or comes back, or swelling and warmth near the joint, can be signs that the joint isn’t healing as expected. Another operation may be needed. Cleveland Clinic says this is rare.[1]
- Bone not growing across the joint. NICE’s committee noted that the procedure stabilizes the joint, but there was evidence that the joint doesn’t fuse in many patients.[3]
- Implant problems. Reported problems include implants placed in the wrong position or pressing on a nerve, which can mean revision surgery. Specialists advising NICE said they had heard of implants loosening.[3]
- New pain nearby. Reported complications include new pain in the facet joints of the spine, trochanteric bursitis at the hip and new low back or buttock pain.[3] Rarely, new or worse pain develops in other parts of the back.[1]
- Other reported problems. These include nerve pain, deep wound infections, large hematomas (collections of blood), and blood clots in a leg vein (deep vein thrombosis) or in the lungs (pulmonary embolism).[3]
- A scar. The cuts are usually only a few inches long, so any scar should be small.[1]
How often problems happen depends on the study. In a pooled analysis of 432 patients from 12 studies that NICE reviewed, 13% had a complication, most often a wound problem, and 2% needed revision surgery because an implant was pressing on a nerve root. A separate study of 469 patients found a 4% infection rate at 6 months.[3] A 2022 systematic review found more adverse events after fusion than with nonsurgical care in the first 6 months, and judged that serious problems may be more common in everyday practice than in trials. It put the rate of revision surgery at likely no higher than 3.8% at 2 years.[10] A 2024 meta-analysis of the trials found no significant difference in adverse events between fusion and nonsurgical care over 2 years of follow-up.[5]
Does SI joint fusion work? What the research shows
Two earlier randomized trials compared minimally invasive fusion with nonsurgical care, and both found fusion more effective. Neither was blinded: patients knew which treatment they’d had.[6][7] In the larger, a US trial of 148 people, 81% of the fusion group met the trial’s definition of success at 6 months, compared with 26% of the nonsurgical group. Success meant pain had dropped by at least 20 points on a 100-point scale, with no serious device-related problem, no worsening nerve symptoms and no repeat surgery.[3] That trial was sponsored by the company that makes the implant it tested. The sponsor ran the statistical analysis, and all the authors conduct research for the company.[6]
A 2024 meta-analysis that pooled 3 trials with 423 people (two randomized against nonsurgical care and one with no comparison group) found fusion led to larger improvements in pain, disability and quality of life than nonsurgical care, but it rated the quality of evidence as low for most outcomes.[5] A 2022 systematic review concluded that, for people with a confirmed diagnosis who haven’t improved with conservative care, fusion is probably more effective than conservative management for pain and physical function.[10] Both reviews drew their effectiveness results mainly from the same two unblinded trials of one type of implant.[5][10]
A double-blind trial at two university hospitals in Norway and Sweden gives a more cautious picture. It randomized 63 people whose SI joint pain had been confirmed by injection to fusion or a sham operation. At 6 months, pain in the operated joint had fallen by 2.6 points on a 0 to 10 scale after fusion and by 1.7 points after sham surgery. The difference wasn’t statistically significant. The authors couldn’t show that fusion was better than sham surgery, and their trial wasn’t designed to prove the two were equal. They concluded that the added effect of fusion appeared low and that a placebo effect might be a large part of the benefit measured after surgery.[7]
At 2 years, people who’d had fusion, including 26 of the 31 in the sham group who chose surgery once they were told, at 6 months, which operation they’d had, reported clear reductions in pain compared with where they started. Because so many crossed over, the trial could no longer measure how fusion compared with sham surgery at that point.[11]
NICE judged the evidence on the safety and efficacy of minimally invasive fusion adequate to support its use, provided standard arrangements for clinical governance, consent and audit are in place. Its committee noted a lack of evidence beyond 3 years of follow-up.[3] That guidance dates from 2017, before the sham-controlled trial was published.[3][7]
The main studies at a glance
| Study | What it found |
|---|---|
| US randomized trial, unblinded: fusion vs nonsurgical care, 148 people, sponsored by the implant maker | 81% vs 26% met the trial’s success measure at 6 months.[3][6] |
| Double-blind trial: fusion vs sham surgery, 63 people | No significant difference in pain at 6 months.[7] |
| 2024 meta-analysis: 2 randomized trials plus 1 single-group trial, 423 people | Better pain, disability and quality of life with fusion. Evidence quality mostly low.[5] |
| 2022 systematic review: 40 studies, of which 2 randomized trials | Probably more effective for pain and function. More adverse events in the first 6 months.[10] |
SI joint fusion recovery
It can take a few months to recover fully. Your surgeon will give you your own recovery timeline and tell you which activities, movements and positions to avoid while you heal.[1]
The first few weeks
Your surgeon will probably tell you to start moving and walking right after the procedure. You might need a walker or a cane to avoid putting too much weight or pressure on the surgery site. Cleveland Clinic’s general advice for the period right after surgery is to:[1]
- walk and move, with a walker or cane if you need one
- avoid lifting more than 10 pounds (4.5 kilograms)
- avoid sitting for more than 45 minutes at a time
- get up and move for around 10 minutes at a time throughout the day
NICE describes a gradual return to full weight bearing over several weeks, using a walker, followed by physical therapy, and notes that people may need crutches for several weeks.[3] Most people need to avoid driving for at least a few weeks, but you should be able to ride in a car or on public transit for short distances right away. Your surgeon will tell you when it’s safe to drive.[1]
Physical therapy and getting back to activity
You might need physical therapy to help you regain your strength. According to Cleveland Clinic, most people can restart all their usual physical activities 3 or 4 months after surgery.[1]
Pain after SI joint fusion
It’s normal to have pain after surgery, especially in the first few weeks. Some of it comes from the operation itself and some from your body starting to heal. Your surgeon will usually suggest a mix of prescription pain medicine, over-the-counter NSAIDs and acetaminophen, and tell you how much of each is safe and how often to take it.[1] Pain that doesn’t get better, comes back or is new is different, and you should tell your surgeon (see the warning signs below).[1] In the evidence NICE reviewed, returning symptoms were one of the reasons people had revision surgery months after the first operation.[3]
When to get medical help
After SI joint fusion, call your surgeon right away if you have:[1]
- a fever higher than 101°F
- bleeding
- signs of infection at the surgery site, such as leaking, swelling, discoloration, a bad smell or warmth
- new or worsening pain
Call 911 or go to the ER if you have back pain and:[9]
- pain, tingling, weakness or numbness in both legs
- loss of feeling around your genitals or anus
- changes in your bladder or bowels, such as trouble urinating or losing control of your bladder or bowels
- changes in how your penis or vagina feels during sex, or trouble getting an erection or reaching orgasm
- chest pain
- pain that started after a serious accident, such as a car crash
Don’t drive yourself to the ER. Ask someone to drive you, or call 911.[9]
Call your doctor right away or go to urgent care the same day if you have back pain and:[9]
- you feel hot, cold, shivery or generally unwell
- the pain is severe and started suddenly, or it’s getting worse quickly
Common questions
Is SI joint fusion a major surgery?
Surgeons usually call joint fusion a major surgery, which means it’s a more complex procedure. Open surgery is usually considered major because more of your body has to be opened up.[1]
What is the success rate of SI joint fusion?
There’s no single figure. Cleveland Clinic says experts estimate that more than 4 out of 5 people who need SI joint fusion get noticeable, lasting pain relief.[1] The trial against sham surgery, though, found no significant difference in pain between fusion and a sham operation at 6 months (see the research section above).[7]
Are there permanent restrictions after SI joint fusion?
Some people have lasting limits in how the joint moves, because two bones have been joined into one, so the joint may not move as freely or smoothly.[1] Cleveland Clinic says you should still be able to return to all your usual physical activities, including exercise and sports, once you’ve recovered.[1]
Can both SI joints be fused?
Yes. NICE says both joints can be treated in the same operation or in separate, staged operations.[3]
Sponsored · Back pain program
Looking for a lower back routine on video?
Get instant access to The Back Pain Breakthrough on any device, and see today’s price on the official site.
Official site · opens in a new tab
Free · From APM Health
Get our free morning movement routine
A short, gentle routine for loosening a stiff back at the start of the day. Sign up now and we’ll email it as soon as it’s ready.
- Free
- Sent as soon as it’s ready
- One email a week at most
Unsubscribe any time. Privacy policy
How we checked this article
Medical review: pending. A clinician hasn’t reviewed this article yet. We last checked it against the sources below on November 6, 2026.
Sources
- Cleveland Clinic. SI (Sacroiliac) Joint Fusion. Last updated July 23, 2025.
- Cleveland Clinic. Sacroiliitis. Last updated August 23, 2023.
- National Institute for Health and Care Excellence (NICE). Minimally invasive sacroiliac joint fusion surgery for chronic sacroiliac pain. Interventional procedures guidance IPG578, now HealthTech guidance HTG436. April 5, 2017.
- Migliorini F, Lucenti L, Bardazzi T, Bell A, Cocconi F, Maffulli N. Management of sacroiliac joint pain: current concepts. Eur J Orthop Surg Traumatol. 2025;35(1):208.
- Ghaddaf AA, Alsharef JF, Alsharef NK, et al. Minimally invasive sacroiliac joint fusion using triangular titanium implants versus nonsurgical management for sacroiliac joint dysfunction: a systematic review and meta-analysis. Can J Surg. 2024;67(1):E16-E26.
- Polly DW, Cher DJ, Wine KD, et al. Randomized controlled trial of minimally invasive sacroiliac joint fusion using triangular titanium implants vs nonsurgical management for sacroiliac joint dysfunction: 12-month outcomes. Neurosurgery. 2015;77(5):674-690.
- Randers EM, Gerdhem P, Stuge B, et al. The effect of minimally invasive sacroiliac joint fusion compared to sham operation: a double-blind randomized placebo-controlled trial. EClinicalMedicine. 2024;68:102438.
- Xu K, Li YL, Xiao SH, Pan YW. Minimally invasive lateral, posterior, and posterolateral sacroiliac joint fusion for low back pain: a systematic review and meta-analysis. J Int Med Res. 2025;53(2):3000605251315300.
- NHS. Back pain. Page last reviewed March 5, 2026.
- Chang E, Rains C, Ali R, Wines RC, Kahwati LC. Minimally invasive sacroiliac joint fusion for chronic sacroiliac joint pain: a systematic review. Spine J. 2022;22(8):1240-1253.
- Kibsgård TJ, Gerdhem P, Diarbakerli E, Randers EM. Minimally invasive sacroiliac joint fusion compared with sham operation (SIFSO trial): a concise follow-up, at 2 years, of a previous report. J Bone Joint Surg Am. 2026;108(18):1445-1452.



